
Master Farhan, an 11-year-old male child, 1st order child born of a non-consanguineous marriage from Hyderabad, Telangana, presented with high continuous fever for 14 days with step-ladder progression, severe apathy, wandering delirium and mumbling speech ("coma vigil") for 3 days, loose greenish-yellow watery stools ("pea-soup diarrhea") for 4 days, progressive abdominal distension, and marked refusal of food.
- Step-ladder pyrexia rising incrementally to a continuous high plateau of $103-104^\circ\text{F}$
- Typhoid state / encephalopathy: muttering delirium, apathy, coma vigil, carphology
- Abdominal distension, pain, and "pea-soup" diarrhea or obstinate constipation
- Intestinal bleeding (sudden hypothermia, melena) or perforation (acute abdomen, shock)
- Toxic myocarditis, hepatitis, or cholecystitis
HOPI
The history is dated back to 14 days ago when the child developed insidious onset of low-to-moderate fever associated with frontal headache, body aches, and dry cough.
Enteric fever (Salmonella enterica serovar Typhi) follows a classical weekly chronological progression: Week 1 (Step-ladder rising pyrexia, bacteremia, constipation/diarrhea), Week 2 (Continuous plateau pyrexia, rose spots, splenomegaly, typhoid state / encephalopathy), and Week 3 (Hypertrophy and necrosis of Peyer's patches $\rightarrow$ Intestinal Hemorrhage and Perforation). Inquire specifically about the source of drinking water, family contacts, relative bradycardia, and neuro-psychiatric alterations.
- Chronological Fever Progression (14 Days Duration):
- Week 1: Fever rose in a step-ladder fashion, each day peaking higher than the previous day, accompanied by malaise, throbbing frontal headache, and anorexia.
- Week 2: Fever became continuous and unyielding, persisting between $103^\circ\text{F}$ and $104^\circ\text{F}$ despite oral paracetamol.
- Neuropsychiatric Manifestations (Typhoid Encephalopathy / Coma Vigil):
- Over the past 3 days, the child lapsed into a toxic, stuporous state: lying motionless with eyes wide open, staring blankly at the ceiling (coma vigil).
- Mutters incoherently to himself and repeatedly picks aimlessly at his bedsheets and clothes (carphology / floccillation) Reflects toxic typhoid encephalopathy driven by systemic endotoxemia and neuro-inflammatory cytokines.
- Gastrointestinal Symptoms:
- Developed 4 to 5 episodes daily of loose, watery, greenish-yellow, foul-smelling stools resembling pea soup (pea-soup diarrhea) for the past 4 days.
- Abdomen became visibly distended with persistent discomfort.
- Negative History:
- No history of sudden, agonizing abdominal pain followed by cold collapse Rules out acute terminal ileal perforation.
- No history of passing massive black tarry stools (melena) or fresh rectal bleeding Rules out major intestinal hemorrhage.
- No history of neck stiffness, photophobia, or focal neurological deficits Differentiates typhoid encephalopathy from acute pyogenic meningitis.
- No history of prior typhoid conjugate vaccination (TCV).
Past History
- No prior history of prolonged fevers or chronic gastrointestinal illnesses.
- No history of hospital admissions or blood transfusions.
Family history
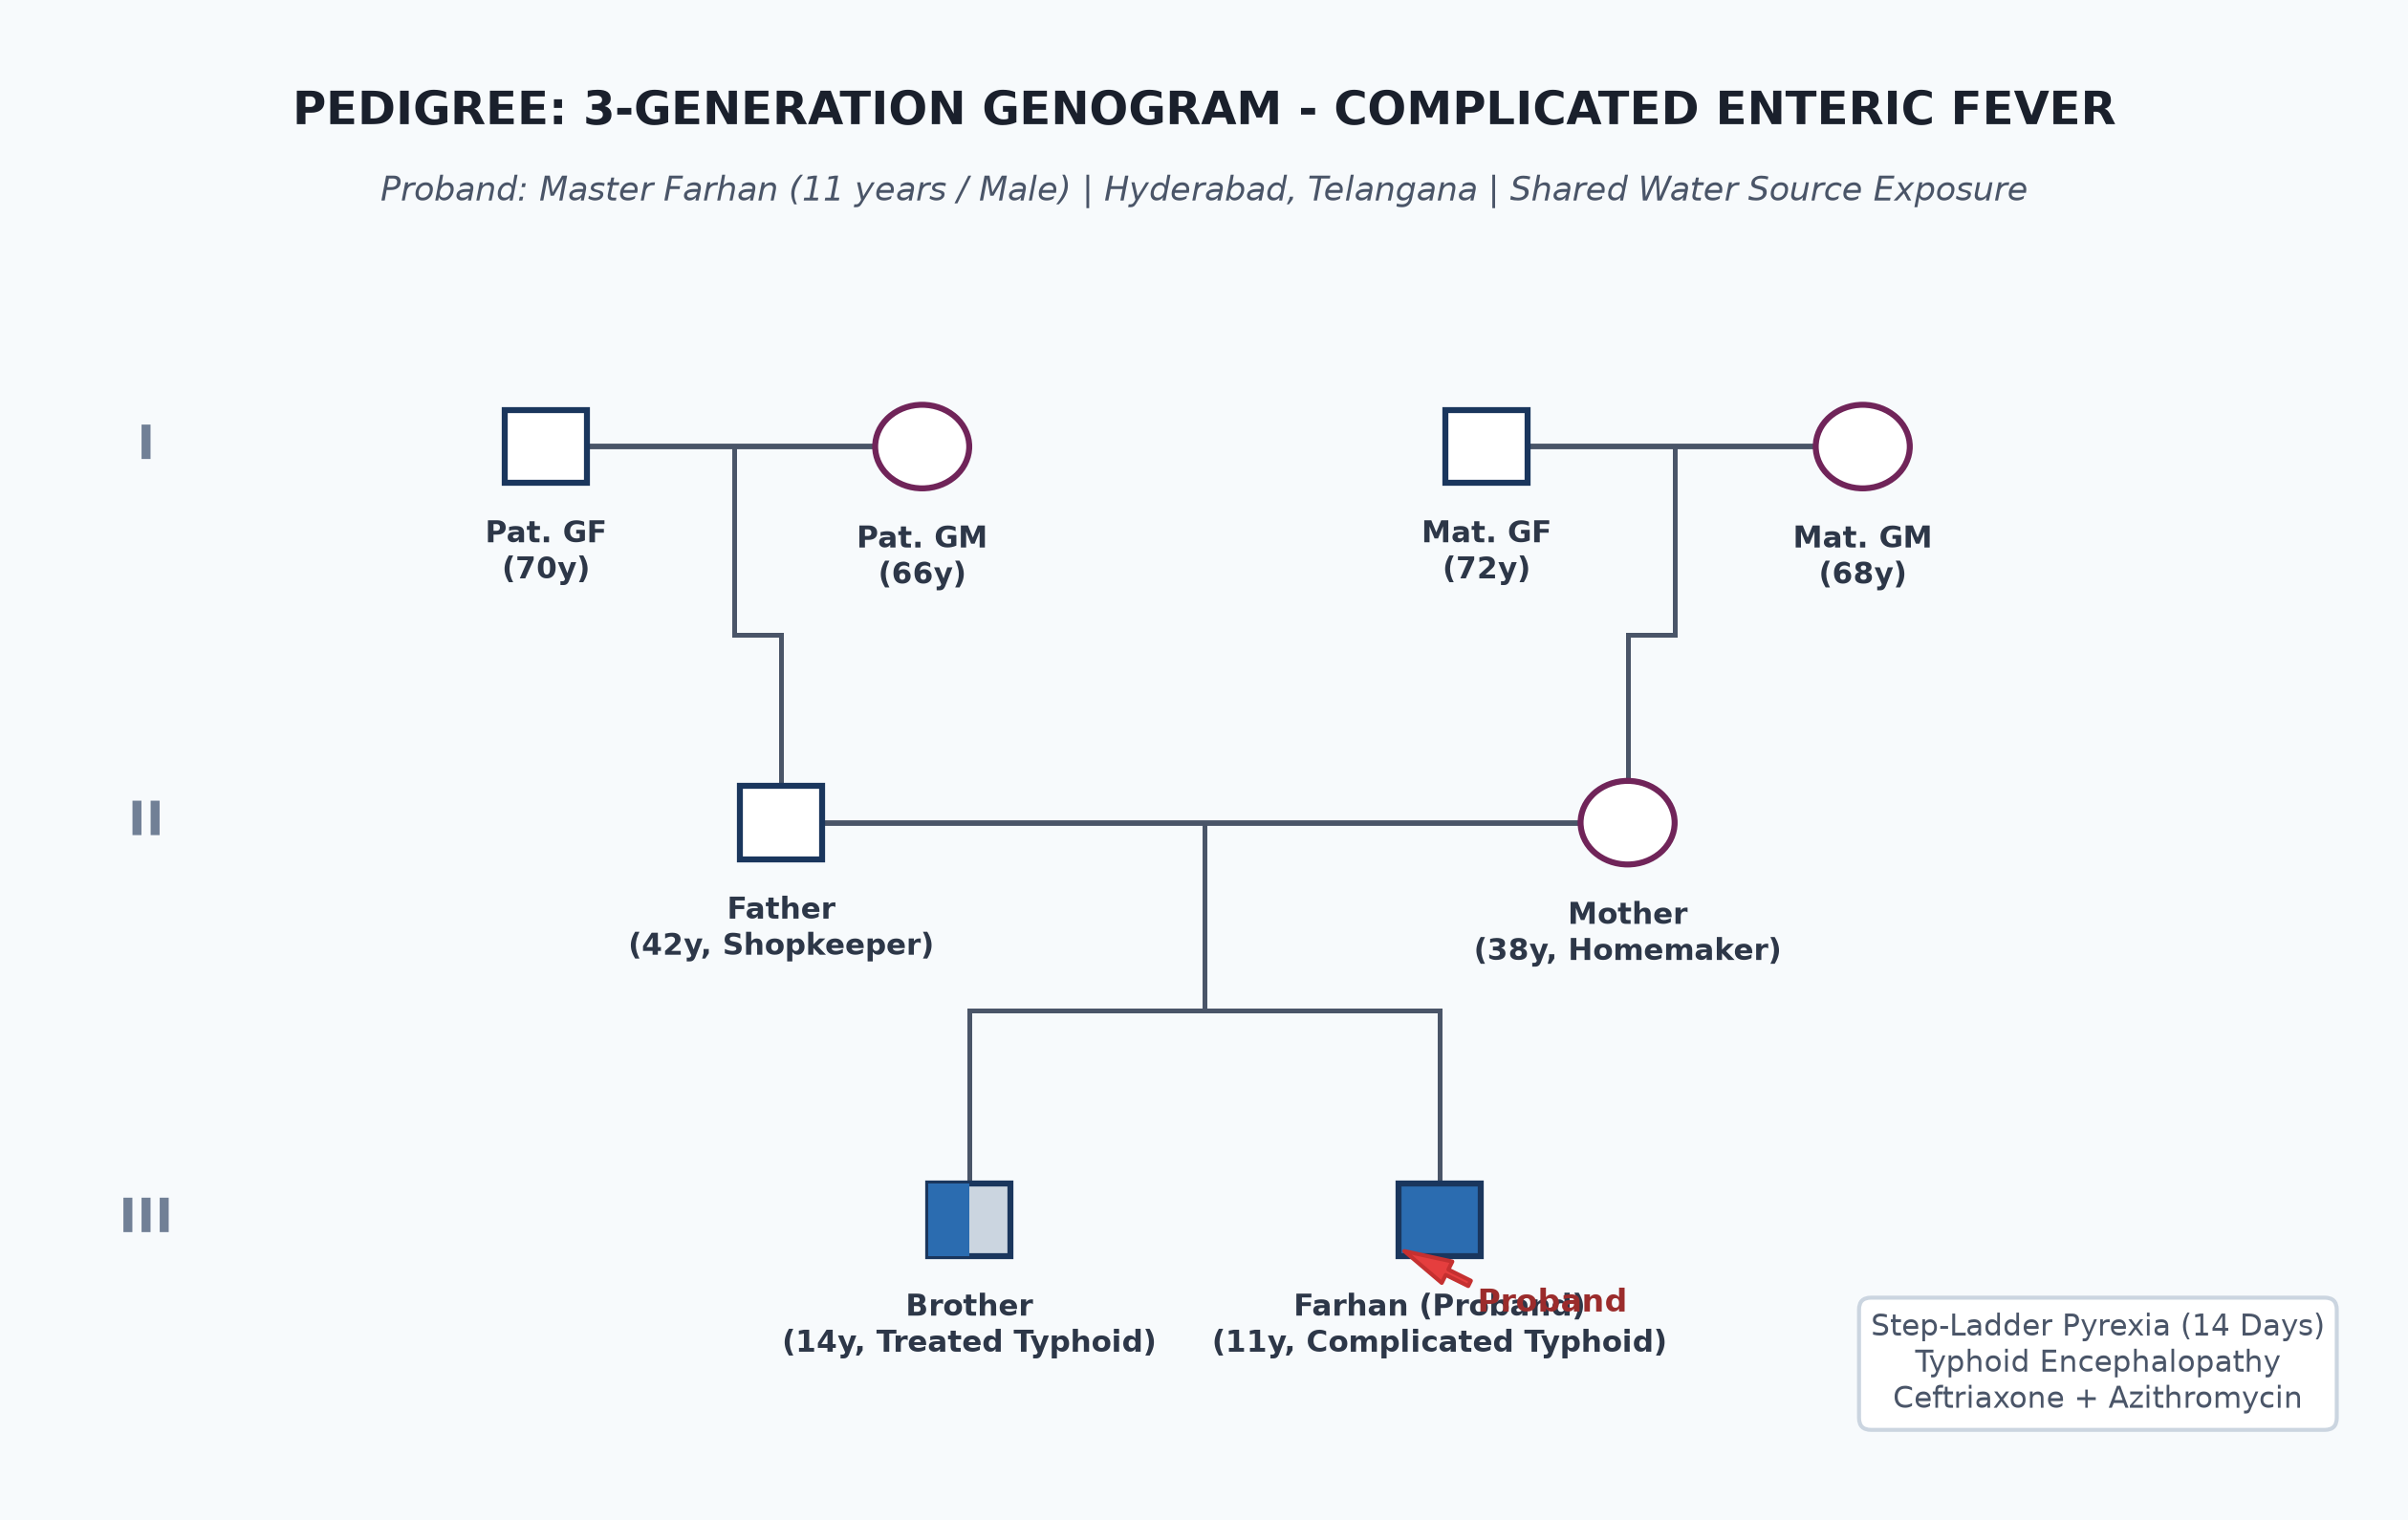
- Born of a non-consanguineous Muslim family.
- Father 42 years, shopkeeper; Mother 38 years, homemaker.
- Household Exposure: Elder brother (14 years old) was treated for culture-proven Salmonella Typhi with oral azithromycin 10 days ago.
- Residence: Urban settlement using municipal piped water which had suffered a drainage pipeline leak 3 weeks ago; family drinks unboiled municipal water.
Immunization history
- Received primary UIP vaccines; has NOT received Typhoid Conjugate Vaccine (TCV).
Dietary history
- Prior to acute illness, consumed a regular mixed home diet. Intake has dropped to near zero over the last 3 days due to encephalopathy.
24-Hour Recall Deficit Analysis
$$ \text{Ideal Body Weight (IBW for 11 years, 50th centile WHO)} = 36.0\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 36 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $36.0\text{ kg} \times 55\text{ kcal/kg} = 1980\text{ kcal}$ | 240 kcal | 1740 kcal | 87.9% Deficit |
| Protein (g) | $36.0\text{ kg} \times 0.95\text{ g/kg} = 34.2\text{ g}$ | 4.0 g | 30.2 g | 88.3% Deficit |
Socioeconomic and KAP
- Modified BG Prasad Socioeconomic Class III (Middle Class).
- Community water contamination episode reported in the neighborhood; parents delayed hospitalization believing it was simple viral pyrexia.
Summary of History
Master Farhan, an 11-year-old male child with household exposure to enteric fever, presents on Day 14 of illness with step-ladder continuous fever, toxic encephalopathy (coma vigil, carphology, muttering delirium), pea-soup diarrhea, and abdominal distension, in the absence of acute peritoneal signs or gross GI hemorrhage.
I would like to consider a provisional diagnosis of Complicated Enteric Fever (Severe Typhoid Fever) with Typhoid Encephalopathy, requiring emergent blood cultures, high-dose IV Ceftriaxone, and adjunctive Dexamethasone therapy.
General head to toe examination
- Behavioral & Neurological Sensorium:
- Lying supine, profoundly apathetic, dull vacant stare (Typhoid facies); mumbling slurred words; purposeful eye contact absent; carphology positive (picking at blankets); Glasgow Coma Scale: 12/15 ($E_3 V_4 M_5$).
- Vitals & Sphygmo-Thermic Dissociation:
- Temperature: $39.8^\circ\text{C}$ ($103.6^\circ\text{F}$).
- Heart Rate: 90 beats/minute, regular, soft volume.
- Viva Hallmark: Relative Bradycardia (Faget Sign): For a body temperature of $103.6^\circ\text{F}$ ($>2.5^\circ\text{F}$ above normal), the heart rate is expected to exceed $125-130\text{ bpm}$ (10 bpm rise per $1^\circ\text{F}$). A heart rate of only $90\text{ bpm}$ represents marked Sphygmo-thermic dissociation, pathognomonic of typhoid fever!
- Respiratory Rate: 22 breaths/minute, regular.
- Blood Pressure: $96/60\text{ mmHg}$ ($50^{\text{th}}$ centile, normotensive).
- Capillary Refill Time: $<2$ seconds.
- Anthropometry:
| Parameter | Observed | Expected (50th WHO) | Centile | Inference |
|---|---|---|---|---|
| Weight | 33.5 kg | 36.0 kg | $50^{\text{th}}\text{ centile}$ | Weight loss ~2.5 kg (~7%) |
| Height | 143.5 cm | 143.5 cm | $50^{\text{th}}\text{ centile}$ | Normal Stature |
- General Physical Findings:
- Oral Cavity (Typhoid Tongue): Heavy, thick, white-to-yellow furring over the dorsum of the tongue, with characteristically clean, fiery red tip and lateral margins.
- Cutaneous Lesions (Rose Spots): Four faint, discrete, salmon-pink, non-itchy blanching macules measuring $2-3\text{ mm}$ identified over the epigastrium and lower chest wall.
- Pallor: Mild pallor of conjunctiva; no icterus, cyanosis, clubbing, or edema.
Systemic Examination
Abdomen
- Symmetrically distended, tympanitic on percussion.
- Palpation: Doughy feel to abdominal wall; moderate tenderness in the right iliac fossa (ileocecal region) with palpable gurgling (borborygmi); no rebound tenderness, no guarding, no wooden rigidity (rules out perforation peritonitis).
- Splenomegaly: Spleen palpable 2.5 cm below left costal margin, soft, smooth, non-tender.
- Hepatomegaly: Liver palpable 2.0 cm below right costal margin, soft, non-tender, span 11.0 cm.
- Auscultation: Active bowel sounds (5-6/minute).
Central Nervous System (CNS)
- Toxic encephalopathy; pupils equal, $3\text{ mm}$, reactive; cranial nerves I-XII grossly intact; motor tone and reflexes normal ($2+$ symmetrical); plantars flexor bilaterally; neck stiffness absent; Kernig sign negative.
Respiratory & Cardiovascular Systems
- Chest clear bilaterally; heart sounds normal, no murmurs.
Summary
Master Farhan, an 11-year-old male child, presents on Day 14 of illness with continuous high-grade fever, relative bradycardia (HR 90 bpm at $103.6^\circ\text{F}$), coated tongue with red edges, rose spots, soft hepatosplenomegaly, right iliac fossa tenderness with gurgling, and toxic typhoid encephalopathy (coma vigil, carphology, GCS 12/15).
Final Clinical Diagnosis: Complicated Enteric Fever (Salmonella enterica serovar Typhi) complicated by Typhoid Encephalopathy, presenting in the second/third week, without intestinal perforation, hemorrhage, or septic shock.
Differential Diagnosis
| Disorder | Points IN FAVOR | Points AGAINST |
|---|---|---|
| Complicated Enteric Fever | Step-ladder fever $>14$ days, relative bradycardia, typhoid tongue, rose spots, hepatosplenomegaly, coma vigil, household contact | Primary Clinical Diagnosis |
| Acute Bacterial / Pyogenic Meningitis | Fever, altered sensorium, delirium | Meningitis features prominent neck rigidity and Kernig sign; relative bradycardia is absent; CSF in typhoid encephalopathy is clear with normal cytology |
| Severe Malaria (Cerebral Malaria) | Fever, splenomegaly, encephalopathy, altered sensorium | Malaria fevers have chills/rigors; features severe anemia, icterus, and tachycardia (not relative bradycardia); peripheral smear is negative for Plasmodium |
| Scrub Typhus with Encephalopathy | Prolonged fever, hepatosplenomegaly, delirium | Absence of pathognomonic eschar; scrub typhus features tachycardia, conjunctival suffusion, and marked capillary leak |
| Acute Appendicitis with Peritonitis | Right iliac fossa tenderness, fever, vomiting | Fever in appendicitis is acute ($1-3$ days), not step-ladder 14 days; features localized guarding and rigidity; lacks splenomegaly or rose spots |
Investigation Protocol & Diagnostic Workup
flowchart TD
    A["Child with 14-Day Step-Ladder Fever, Encephalopathy & Relative Bradycardia"] --> B["Stat Automated Blood Culture (BACTEC: 5-10 mL Blood) & CBC"]
    B --> C["Stat Baseline Widal Test (Tube Agglutination) & Typhidot IgM"]
    C --> D["Erect Abdominal X-Ray (Rule Out Free Gas Under Diaphragm / Perforation)"]
    D --> E{"Pneumoperitoneum Present?"}
    E -->|Yes| F["EMERGENCY SURGICAL LAPAROTOMY (Ileal Perforation Repair)"]
    E -->|No| G["Start High-Dose IV Ceftriaxone (75-100 mg/kg/day) + Oral Azithromycin (20 mg/kg/day)"]
    G --> H{"Typhoid Encephalopathy / Stupor Present?"}
    H -->|Yes| I["Add High-Dose IV Dexamethasone (3 mg/kg bolus, then 1 mg/kg Q6H x 48 hr)"]
1. Microbiological & Serological Confirmation
- Automated Blood Culture (BACTEC FX):
- Flagged positive at 28 hours of incubation.
- Subculture demonstrates non-lactose fermenting colonies with black centers on Salmonella-Shigella (SS) agar.
- Automated Identification (VITEK-2): Confirms Salmonella enterica serovar Typhi.
- Antibiotic Sensitivity: Sensitive to Ceftriaxone, Azithromycin, and Meropenem; resistant to Ampicillin, Chloramphenicol, and Co-trimoxazole (MDR strain); Ciprofloxacin non-susceptible (MIC $>0.5\text{ mcg/mL}$).
- Quantitative Widal Tube Agglutination Test (Day 14):
- Somatic O (TO) Titer: $1:320$ (Diagnostic cutoff in India $\ge 1:160$).
- Flagellar H (TH) Titer: $1:320$ (Diagnostic $\ge 1:160$).
2. Hematological & Metabolic Panel
- Complete Blood Count:
- Total Leukocyte Count: $3800/\mu\text{L}$ (Leukopenia with absence of eosinophils $\rightarrow$ Aneosinophilia is a classic typhoid clue).
- Hemoglobin: $10.4\text{ g/dL}$.
- Platelet Count: $160,000/\mu\text{L}$.
- Liver & Renal Function Tests:
- AST $88\text{ U/L}$, ALT $74\text{ U/L}$ (Mild transaminitis / typhoid hepatitis).
- Serum Bilirubin: $0.8\text{ mg/dL}$.
- Serum Creatinine: $0.5\text{ mg/dL}$, BUN $16\text{ mg/dL}$.
3. Abdominal Radiography (Perforation Rule-Out)
- Erect Plain Radiograph of Chest & Upper Abdomen:
- No free subdiaphragmatic crescent of gas (excludes pneumoperitoneum / intestinal perforation).
- Mild gaseous distension of small bowel loops.
Therapeutic Management Protocol (IAP Infectious Disease Guidelines)
1. Dual Antimicrobial Regimen for Complicated MDR Enteric Fever
- Intravenous Ceftriaxone:
- Dose: $100\text{ mg/kg/day}$ divided into two equal doses every 12 hours (Q12H) IV ($1700\text{ mg}$ IV Q12H for this $33.5\text{ kg}$ child).
- Duration: 10 to 14 days.
- Oral Azithromycin (Synergistic Co-Administration):
- Dose: $20\text{ mg/kg/day}$ orally as a single daily dose ($670\text{ mg}$ OD, max 1000 mg) for 7 days.
- Rationale: Excellent intracellular accumulation within reticuloendothelial macrophages and concentration in gallbladder bile; eradicates biliary carriage and prevents relapses.
2. Adjunctive Corticosteroid Therapy for Typhoid Encephalopathy
- Indication: Severe enteric fever with altered consciousness (delirium, stupor, coma vigil).
- Intravenous Dexamethasone Protocol:
- Initial Bolus: $3.0\text{ mg/kg}$ IV over 30 minutes ($100\text{ mg}$ stat).
- Maintenance: $1.0\text{ mg/kg}$ IV every 6 hours for a total of 48 hours (8 doses).
- Evidence: Reduces mortality from $50\%$ down to $10\%$ in typhoid encephalopathy without increasing intestinal perforation risk!
3. Supportive & Monitoring Protocol
- Strict enteric precautions.
- Bedside observation for sudden drop in temperature, tachycardia, or abdominal guarding (signs of intestinal perforation or hemorrhage).
- Defervescence is expected in 4 to 6 days of starting effective cephalosporin therapy.