
Master Arjun, a 7-year-old male child, 1st order child born of a non-consanguineous marriage from Varanasi, Uttar Pradesh, presented with complaints of an acute, non-itchy red-purple raised rash over both lower legs and buttocks for 5 days, severe colicky periumbilical abdominal pain with two episodes of blood-stained loose stools for 3 days, and swelling and pain in both ankles for 4 days, preceded by a sore throat and low-grade fever 2 weeks ago.
- Raised, palpable, non-thrombocytopenic purpura over gravity-dependent lower extremities and buttocks
- Colicky periumbilical abdominal pain with vomiting or melena/hematochezia
- Acute, painful periarticular swelling of knees and ankles without joint effusion
- Hematuria (tea-colored or smoky urine) and facial puffiness (HSP nephritis)
- Painful, tender scrotal swelling (scrotal vasculitis) mimicking testicular torsion
HOPI
The history is dated back to 2 weeks ago when the child had an episode of upper respiratory tract infection (sore throat, rhinorrhea, low fever) which subsided with symptomatic antipyretics.
IgA Vasculitis is the commonest systemic vasculitis of childhood, characterized by IgA1-immune complex deposition in small postcapillary venules. The diagnosis is clinical, anchored by palpable purpura with lower limb predominance. In the history, probe the 4 classic organ systems: Skin (gravity-dependent extensor purpura), Musculoskeletal (periarticular non-erosive swelling), Gastrointestinal (colicky pain from bowel wall ischemia, GI bleeding, intussusception), and Renal (hematuria, proteinuria, hypertension).
- Cutaneous Rash (Palpable Purpura):
- Appeared 5 days ago, initially around both ankles and shins, spreading upwards to thighs and buttocks.
- Completely spared the trunk, chest, neck, and face.
- Lesions began as erythematous macules/urticarial wheals which transformed into raised, dark purple, palpable nodules and petechiae measuring 2 to 8 mm.
- Completely non-pruritic, non-tender, and do not fade on pressure Points to leukocytoclastic vasculitis with erythrocyte extravasation into the dermis.
- Severe Colicky Abdominal Pain & GI Bleeding:
- Developed 3 days ago; severe, episodic, cramping periumbilical pain causing the child to curl into a fetal position.
- Followed by 2 episodes of passing loose stools mixed with dark red blood and mucus Reflects mucosal and submucosal ischemia, hemorrhage, and bowel wall edema.
- Mother noted no bilious vomiting or visible abdominal lump.
- Joint Symptoms (Arthritis/Arthralgia):
- Noticed 4 days ago; acute, painful swelling around both ankles, accompanied by refusal to walk or bear weight.
- Periarticular swelling; skin overlying ankles was puffy but not warm or red.
- Urinary Symptoms (Renal Involvement):
- Mother noticed the urine appeared slightly smoky and dark over the last 2 days. No burning micturition, no gravel.
- Negative History:
- No history of epistaxis, bleeding from gums, or unprovoked hematomas Rules out Immune Thrombocytopenia (ITP) and bleeding disorders.
- No history of high-grade unyielding fever or strawberry tongue Rules out Kawasaki Disease.
- No history of malar rash, oral ulcers, or photosensitivity Rules out Systemic Lupus Erythematosus.
- No history of sudden, agonizing scrotal pain or testicular swelling Rules out scrotal vasculitis or acute testicular torsion.
Past History
- No prior history of similar purpuric skin rashes, bloody diarrhea, or renal disease.
- Had mild bronchial asthma treated with inhaled salbutamol as needed.
Family history
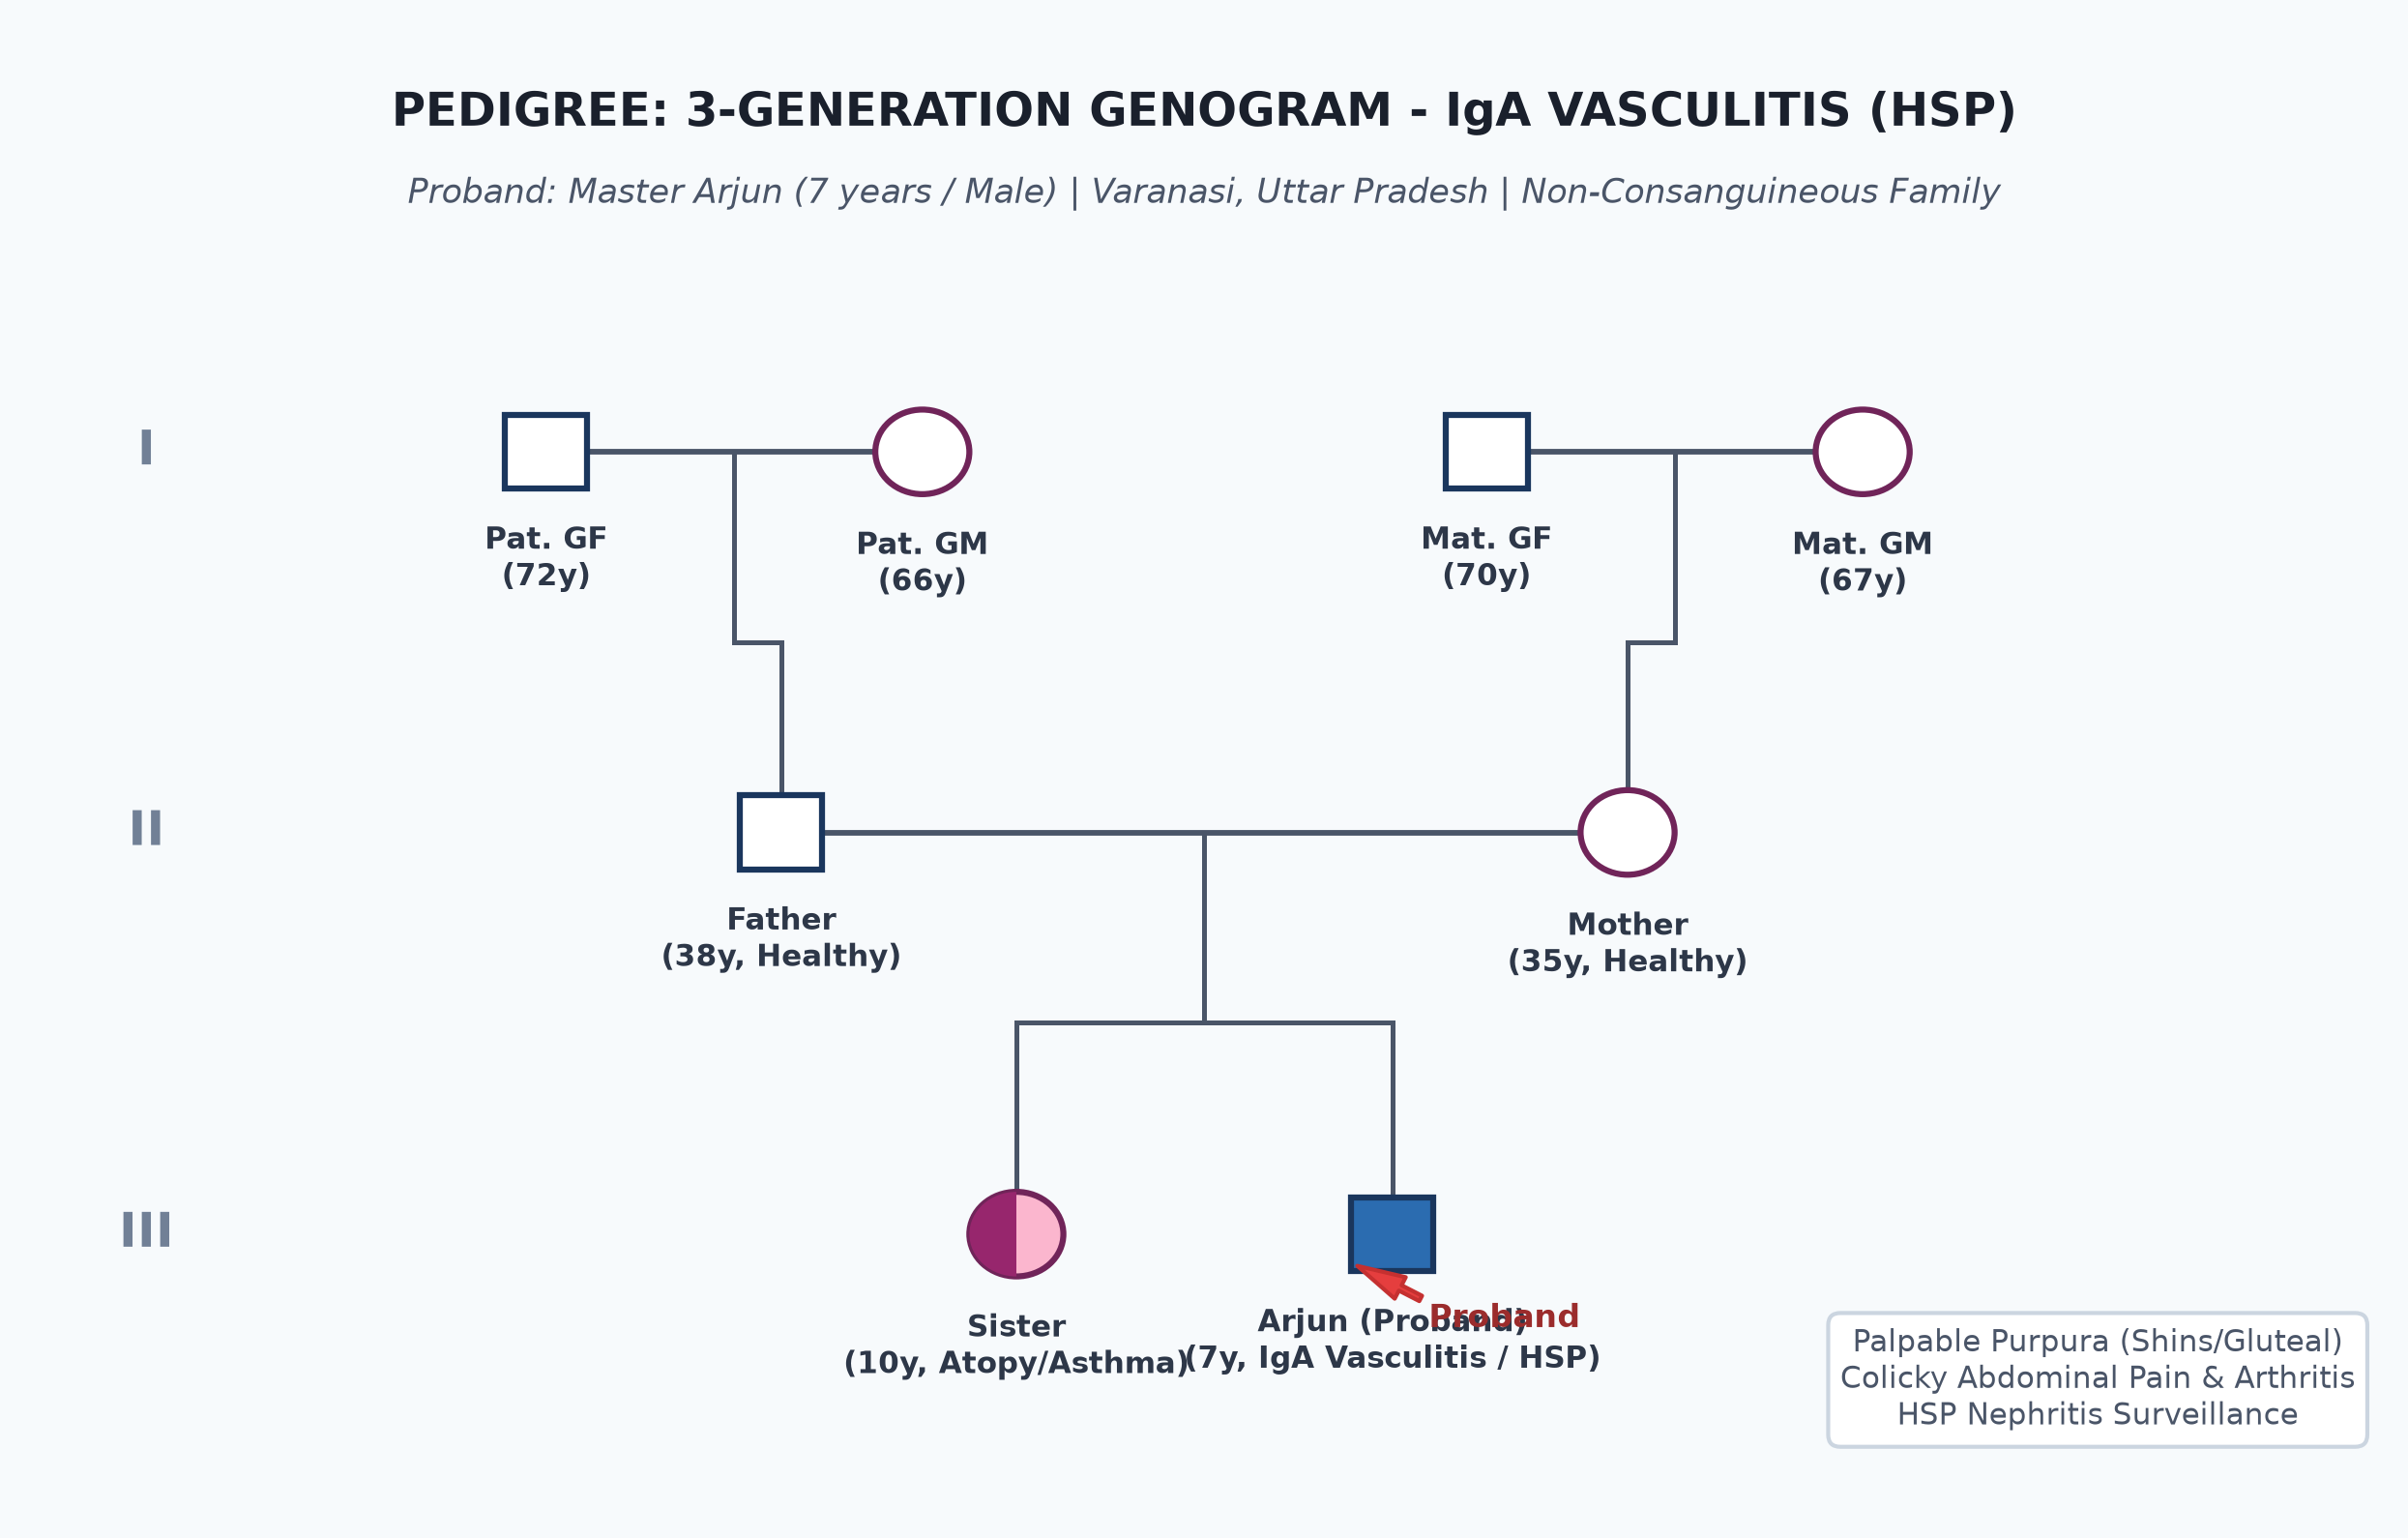
- Non-consanguineous marriage.
- Father 38 years, school teacher; Mother 35 years, homemaker; both healthy.
- Elder sister (10 years old) has atopic dermatitis and allergic rhinitis.
Immunization history
- Fully immunized up to age according to the National Immunization Schedule.
Dietary history
- Consumes a standard mixed home diet meeting 100% of ICMR-NIN RDA for age.
24-Hour Recall Deficit Analysis
$$ \text{Ideal Body Weight (IBW for 7 years, 50th centile WHO)} = 23.0\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 23 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $23.0\text{ kg} \times 65\text{ kcal/kg} = 1495\text{ kcal}$ | 1020 kcal | 475 kcal | 31.8% Deficit |
| Protein (g) | $23.0\text{ kg} \times 0.98\text{ g/kg} = 22.5\text{ g}$ | 16.2 g | 6.3 g | 28.0% Deficit |
Socioeconomic and KAP
- Modified BG Prasad Socioeconomic Class II (Upper Middle Class).
- Parents panicked by the appearance of "blood spots" and bloody stools; seeking urgent hospital care.
Summary of History
Master Arjun, a 7-year-old male child, presents with a 5-day history of post-infectious palpable purpura over gravity-dependent lower limbs and buttocks, acute colicky abdominal pain with bloody stools, bilateral ankle periarticular arthritis, and smoky urine, in the absence of mucosal bleeding or thrombocytopenia.
I would like to consider a provisional diagnosis of IgA Vasculitis (Henoch-Schönlein Purpura) presenting with the classical tetrad of palpable purpura, arthritis, gastrointestinal vasculitis, and active HSP nephritis.
General head to toe examination
- Behavioral State: Prechtl State 3 (alert, cooperative, curling up occasionally during bouts of abdominal colic).
- Vitals:
- Heart Rate: 98 beats/minute, regular, good volume.
- Respiratory Rate: 20 breaths/minute, regular.
- Blood Pressure: $112/74\text{ mmHg}$ ($90^{\text{th}}\text{ to } 95^{\text{th}}$ centile $\rightarrow$ Pre-hypertensive / Early Hypertension secondary to active glomerulonephritis).
- Temperature: $37.0^\circ\text{C}$ (afebrile).
- Capillary Refill Time: $<2$ seconds.
- Anthropometry:
| Parameter | Observed | Expected (50th WHO) | Centile | Inference |
|---|---|---|---|---|
| Weight | 22.8 kg | 23.0 kg | $50^{\text{th}}\text{ centile}$ | Normal nutrition |
| Height | 122.0 cm | 122.0 cm | $50^{\text{th}}\text{ centile}$ | Normal Stature |
| BMI | $15.3\text{ kg/m}^2$ | $15.5\text{ kg/m}^2$ | $50^{\text{th}}\text{ centile}$ | Normal |
- Comprehensive Dermatological Examination:
- Palpable Purpura: Extensive, raised, non-blanching, discrete and confluent purpuric macules and plaques measuring 2 to 10 mm.
- Anatomical Distribution: Strictly symmetrical, concentrated over the extensor surfaces of the lower extremities (dorsum of feet, malleoli, pretibial area, knees) and buttocks.
- Spared Areas: Complete absence of lesions on the trunk, palms, soles, neck, and face.
- Edema: Mild non-pitting periarticular subcutaneous edema overlying the dorsum of both feet and ankles.
Musculoskeletal Examination
- Ankles (Bilateral): Tender periarticular soft tissue swelling; active and passive dorsiflexion eliciting pain; no true intra-articular effusion (absence of fluid fluctuation); no erythema.
- Knees & Wrists: Full range of motion, non-tender.
Systemic Examination
Abdomen
- Symmetrically flat, moves with respiration.
- Palpation: Soft, generalized mild tenderness, maximal in the periumbilical region; no localized right iliac fossa tenderness, no muscular rigidity, no rebound tenderness; no palpable sausage-shaped abdominal mass (rules out ileocolic intussusception).
- Organomegaly: Liver palpable 1.0 cm below costal margin, soft; spleen not palpable.
- Auscultation: Hyperactive bowel sounds (6-8/minute).
- Digital Rectal Examination: Stool on glove is brown, streaked with dark red blood; stool occult blood test positive.
Cardiovascular, Respiratory & Genitourinary Systems
- CVS & RS: Clinically normal.
- Genitalia: Scrotum normal, non-swollen, non-tender; testes palpable bilaterally, normal volume, non-tender (excludes acute scrotal vasculitis).
Summary
Master Arjun, a 7-year-old male child, presents with the classic clinical tetrad of IgA Vasculitis fulfilling the EULAR/PRINTO/PRES consensus criteria: mandatory non-thrombocytopenic palpable purpura on lower limbs and buttocks, colicky abdominal pain with hematochezia, bilateral ankle periarticular arthritis, and elevated blood pressure ($112/74\text{ mmHg}$) with smoky urine indicating active glomerulonephritis.
Final Clinical Diagnosis: IgA Vasculitis (Henoch-Schönlein Purpura), presenting with acute gastrointestinal vasculitis and active HSP Nephritis (microscopic hematuria, proteinuria, pre-hypertension), without intussusception or acute kidney injury.
Differential Diagnosis
| Disorder | Points IN FAVOR | Points AGAINST |
|---|---|---|
| IgA Vasculitis (HSP) | Palpable purpura (shins/buttocks), normal platelets, colicky abdominal pain, ankle arthritis, hematuria | Primary Clinical Diagnosis |
| Immune Thrombocytopenia (ITP) | Purpuric skin lesions, male child | ITP purpura is flat/macular (not palpable), randomly distributed over trunk and face; platelet count is severely reduced ($<20,000/\mu\text{L}$); lacks arthritis, abdominal pain, or nephritis |
| Acute Glomerulonephritis (PSGN) | Post-pharyngitic onset, hematuria, hypertension | PSGN lacks palpable purpuric rash, colicky abdominal pain, hematochezia, or arthritis; complement C3 is low in PSGN (normal in HSP) |
| Meningococcemia | Acute purpuric rash, fever, lethargy | Child is afebrile, non-toxic; meningococcemia features rapid progression to fulminant shock, DIC, purpura fulminans, and high fever |
| Acute Appendicitis / Intussusception | Severe colicky abdominal pain, vomiting, bloody stools | Does not account for symmetrical lower limb palpable purpura or ankle arthritis; purpura precedes or accompanies abdominal signs |
Investigation Protocol & Diagnostic Workup
flowchart TD
    A["Child with Palpable Purpura, Abdominal Pain & Arthritis"] --> B["Stat CBC, Platelet Count & Coagulation Profile (PT/INR/aPTT)"]
    B --> C{"Platelets Normal or Elevated (> 150,000) & Coagulation Normal?"}
    C -->|Yes| D["Confirm Non-Thrombocytopenic Purpura (IgA Vasculitis)"]
    D --> E["Stat Urinalysis & Spot UPCR: Screen for HSP Nephritis"]
    E --> F{"Hematuria > 5 RBCs/HPF OR Proteinuria UPCR > 0.5?"}
    F -->|Yes| G["Stage HSP Nephritis: RFT, Blood Pressure, 24-hr Urine Protein"]
    F -->|No| H["Serial Weekly Urinalysis & BP Surveillance for 6 Months"]
    G --> I{"Nephrotic Proteinuria (UPCR > 2) OR Elevated Creatinine?"}
    I -->|Yes| J["Indication for Renal Biopsy (ISKDC Staging) & Corticosteroids"]
1. Hematology & Coagulation
- Platelet Count: $380,000/\mu\text{L}$ (Completely normal / reactive; definitively confirms non-thrombocytopenic purpura).
- Hemoglobin: $11.8\text{ g/dL}$; TLC: $11,200/\mu\text{L}$ ($68\%$ neutrophils).
- Coagulation Profile: Prothrombin Time (PT) $12.4\text{ sec}$, INR $1.02$, aPTT $28.0\text{ sec}$ (Normal; rules out bleeding diathesis).
2. Urinalysis & Renal Function Tests (HSP Nephritis Staging)
- Urine Routine & Microscopy:
- Protein: $2+$ on dipstick ($100\text{ mg/dL}$).
- Red Blood Cells: $25-30\text{ RBCs/HPF}$ (Dysmorphic erythrocytes with red cell casts $\rightarrow$ confirms glomerular hematuria).
- Absence of glycosuria, nitrites, or pus cells.
- Spot Urine Protein-to-Creatinine Ratio (UPCR): $1.1\text{ mg/mg}$ (Significant non-nephrotic proteinuria; normal $<0.2\text{ mg/mg}$).
- Renal Function Tests: Serum Creatinine $0.48\text{ mg/dL}$ (Normal for 7y), BUN $14\text{ mg/dL}$, Serum Albumin $3.6\text{ g/dL}$, Serum Electrolytes normal.
- Serum Complement C3 and C4: Normal (C3 $112\text{ mg/dL}$, C4 $28\text{ mg/dL}$; rules out PSGN and Lupus).
3. Abdominal Imaging
- High-Resolution Abdominal Ultrasonography:
- Prominent bowel wall thickening ($4.5\text{ mm}$) with submucosal edema in the terminal ileum and cecum.
- No target or donut sign (definitively excludes ileo-ileal or ileocolic intussusception).
- Kidneys bilaterally normal in size and echogenicity.
Therapeutic Management Protocol
1. Management of Gastrointestinal & Articular Manifestations
- Short-Course Corticosteroids (For Severe Abdominal Pain & Arthritis):
- Oral Prednisolone: $1.0\text{ to } 2.0\text{ mg/kg/day}$ ($25-30\text{ mg/day}$) orally for 1 to 2 weeks, followed by a rapid taper over 2 weeks.
- Clinical Evidence: Steroids dramatically reduce intestinal submucosal edema, relieve severe colicky pain, resolve GI bleeding, and accelerate joint recovery.
- Viva Trap Warning: Corticosteroids do NOT prevent the development or progression of HSP nephritis! Prophylactic steroids should never be given to prevent kidney disease.
- Analgesia: Acetaminophen (Paracetamol $15\text{ mg/kg/dose}$) as needed. (Avoid NSAIDs due to active GI mucosal bleeding and concurrent glomerulonephritis).
2. Management of HSP Nephritis
- Renoprotection & Blood Pressure Control:
- Initiate oral ACE Inhibitor (Enalapril at $0.1-0.2\text{ mg/kg/day}$) to reduce glomerular hyperfiltration, control pre-hypertension, and suppress proteinuria.
- Long-Term Monitoring Protocol (Mandatory 6-Month Rule):
- Urine dipstick and blood pressure checks weekly for Month 1, every 2 weeks for Months 2 and 3, and monthly up to 6 months.
- If proteinuria resolves and urinalysis is clear at 6 months, long-term renal prognosis is excellent.