
Master Ishan, a 7-year-old male child, 2nd order offspring born of a 2nd-degree consanguineous marriage from Cuttack, Odisha, presented with complaints of progressive insidious pallor and easy fatigability for 3 months, recurrent spontaneous gum bleeding and epistaxis for 6 weeks, multiple large bluish bruises over the limbs following trivial trauma for 1 month, and low-grade intermittent fever for 10 days, in the absence of any bone pain, joint swellings, jaundice, or abdominal distension.
- Insidious, progressive pallor, weakness, and exercise intolerance (Severe anemia)
- Mucocutaneous bleeding: epistaxis, gingival bleeding, petechiae, and ecchymoses (Thrombocytopenia)
- Recurrent bacterial infections, oral ulcerations, or febrile episodes (Neutropenia)
- Congenital skeletal anomalies: hypoplastic or absent thumbs, short stature, and microcephaly (Fanconi phenotype)
- Cutaneous pigmentary changes: generalized bronze hyperpigmentation and café-au-lait macules
- Striking ABSENCE of lymphadenopathy, hepatosplenomegaly, or bone pain (Differentiates from leukemia)
HOPI
The child was in his usual state of health until 3 months ago when his mother noted that he was becoming gradually pale, lethargic, and reluctant to play outdoors with peers.
Aplastic anemia is characterized by primary hematopoietic stem cell failure yielding an 'empty' hypocellular marrow. In contrast to acute leukemia, the onset is characteristically insidious. The hallmark physical feature separating Aplastic Anemia from ALL is the complete absence of lymphadenopathy, hepatosplenomegaly, and bone tenderness. In every child presenting with aplastic anemia, meticulously examine for dysmorphic features of Fanconi Anemia (FA): thumbs (hypoplastic/absent/bifid), radial ray defects, café-au-lait macules, short stature, and microcephaly. Bone marrow failure in Fanconi anemia typically manifests between 5 and 10 years of age!
- Insidious Progressive Pallor & Fatigability:
- Began 3 months ago; mother noted yellow-pale discoloration of conjunctiva, palms, and soles.
- Exertional breathlessness when climbing one flight of stairs; child complains of dizziness on standing.
- Mucocutaneous Bleeding Diathesis:
- Developed 6 weeks ago; frequent spontaneous oozing from gums during toothbrushing.
- Three discrete episodes of anterior epistaxis requiring nasal packing.
- Large ecchymotic patches appearing over the shins, buttocks, and arms after minor bumps.
- Intermittent Low-Grade Fever:
- Documented over the past 10 days; temperature up to $100.4^\circ\text{F}$ ($38.0^\circ\text{C}$), responding to paracetamol; no localized focus of infection.
- Negative Inquiries:
- No history of antecedent jaundice, viral hepatitis, or blood transfusions.
- No history of chloramphenicol, carbamazepine, sulfonamide, or pesticide/chemical exposure.
- No bone or joint pains, no morning stiffness, and no refusal to walk.
- No dark-colored urine or jaundice (rules out Paroxysmal Nocturnal Hemoglobinuria [PNH] or autoimmune hemolytic anemia).
Past history
- History of low birth weight (2.1 kg at term) with congenital deformity of the right thumb noticed since birth.
- No history of major surgeries, previous blood product transfusions, or prolonged hospital stays.
Antenatal, natal and postnatal history
- Born to a 24-year-old primigravida mother; regular antenatal care; first-trimester ultrasound showed fetal growth lag.
- Full-term normal vaginal delivery at district hospital; birth weight 2.1 kg (SGA $<10^{\text{th}}$ percentile); cried immediately.
- Congenital anomaly: Right thumb was small, rudimentary, and hypoplastic.
- Mother had one spontaneous early miscarriage at 10 weeks of gestation prior to this pregnancy.
Development history
- Mild global developmental delay in early motor milestones: Sat unassisted at 9 months, walked independently at 17 months.
- Language and social milestones were age-appropriate: single words with meaning at 12 months, sentences at 2.5 years.
- Attends primary school; academic performance is average.
Family history
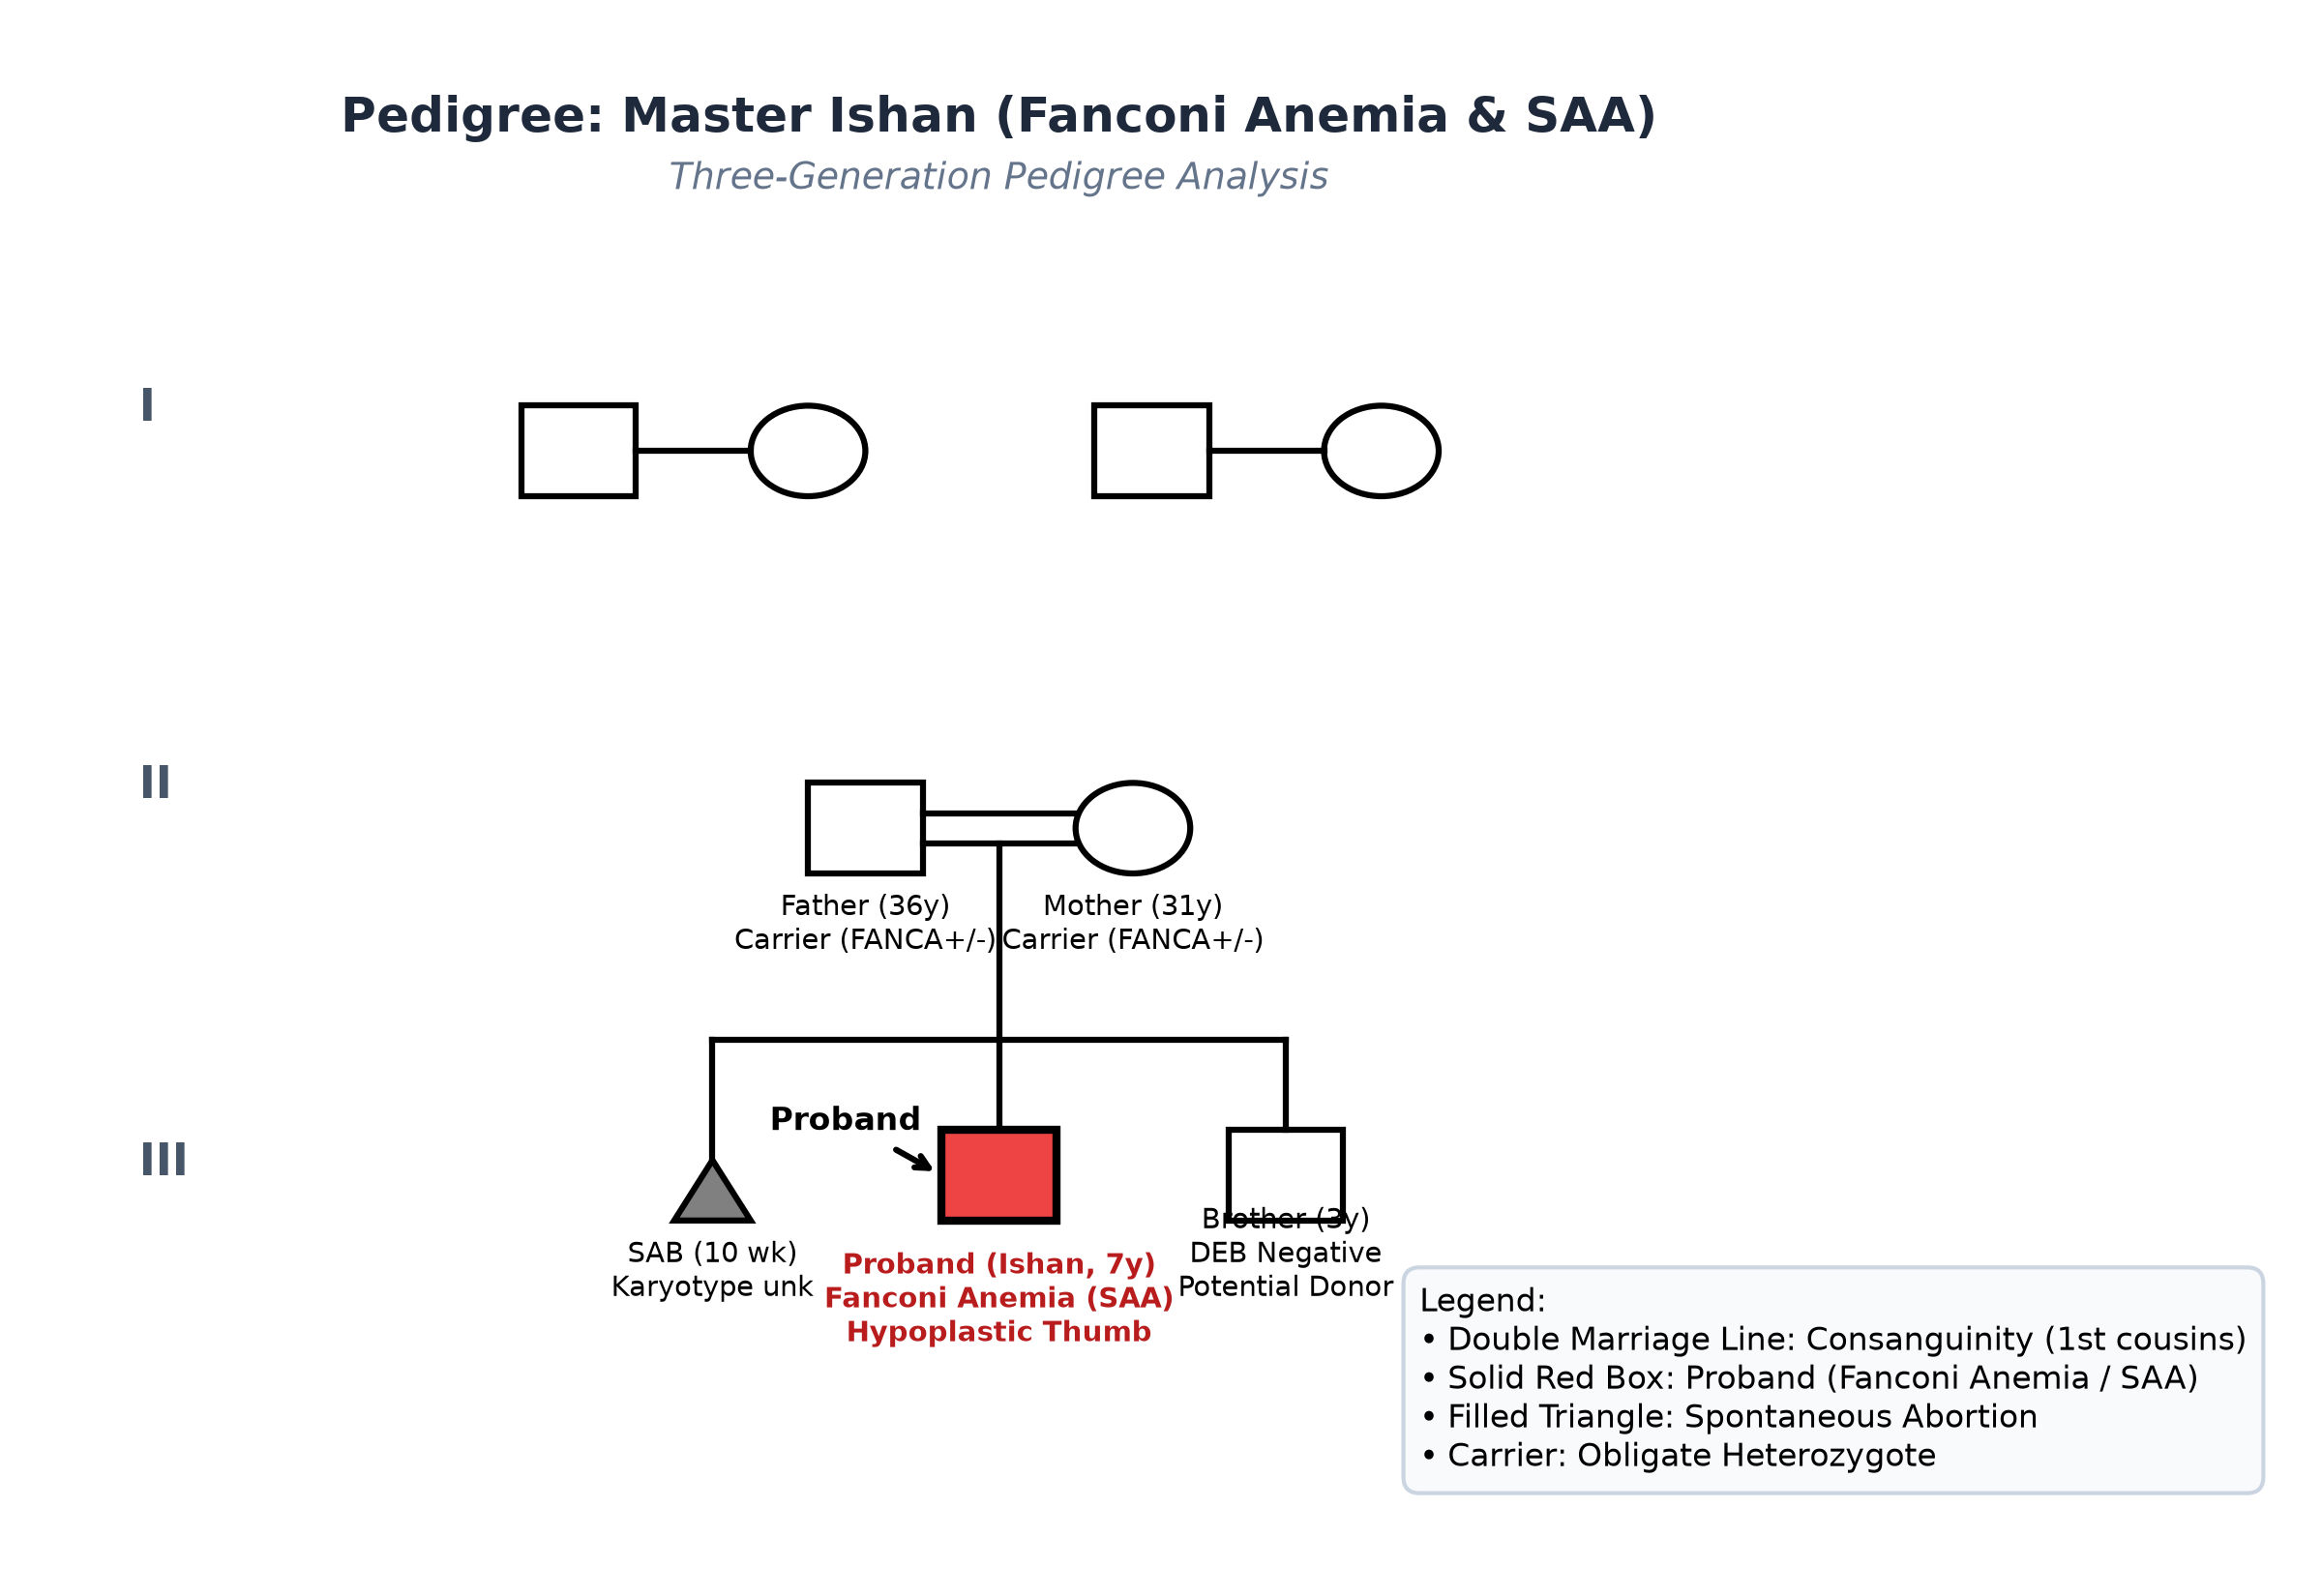
- Parents are first cousins (second-degree consanguinity).
- Father 36 years, laborer; Mother 31 years, homemaker; both clinically healthy.
- Mother had 1 first-trimester spontaneous miscarriage.
- Younger brother (3 years old) is clinically healthy with normal hands and normal CBC.
- No family history of early deaths, recurrent cytopenias, leukemia, or gynecological cancers.
Immunization history
- Received age-appropriate vaccines per the National Immunization Schedule; no adverse events.
Dietary history
- Consumes a mixed rice-dal based diet with inadequate vegetables and dairy.
| Food Item | Quantity | Calories (kcal) | Protein (g) |
|---|---|---|---|
| Cow's Milk (toned) | 200 mL | 120 | 6.4 |
| Boiled Rice | 120 g cooked | 156 | 3.2 |
| Roti (whole wheat, 1) | 30 g flour | 102 | 3.5 |
| Toor Dal (watery, 1 katori) | 25 g raw | 85 | 5.5 |
| Potato / Mixed Sabzi | 1 small bowl | 90 | 1.8 |
| Puffed Rice (Murmura) | 30 g | 110 | 2.0 |
| Biscuit / Rusk | 2 pieces | 80 | 1.2 |
| Total Observed Daily Intake | — | 743 kcal | 23.6 g |
24-Hour Recall Deficit Analysis
$$ \text{Ideal Body Weight (IBW for 7 years, 50th centile WHO)} = 23.0\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 23.0 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $23.0\text{ kg} \times 62\text{ kcal/kg} = 1426\text{ kcal}$ | 743 kcal | 683 kcal | 47.9% Deficit |
| Protein (g) | $23.0\text{ kg} \times 0.95\text{ g/kg} = 21.85\text{ g}$ | 23.6 g | Nil (Adequate) | 0% Deficit |
The expected calories and proteins should be calculated from the ideal body weight, not from current weight.
Socioeconomic and KAP
- Modified BG Prasad Socioeconomic Class IV (Lower Middle Class).
- Lives in a semi-pucca rural dwelling; water from community tubewell.
Summary of History
Master Ishan, a 7-year-old male child born of consanguineous parents with low birth weight and a congenital right thumb anomaly, presents with a 3-month insidious history of severe anemia, thrombocytopenic mucocutaneous bleeding, and low-grade neutropenic fever, without lymphadenopathy, organomegaly, or bone pain.
I would like to consider a provisional diagnosis of Severe Aplastic Anemia (SAA), highly suspicious for an underlying Inherited Bone Marrow Failure Syndrome (Fanconi Anemia) given the consanguinity, short stature, microcephaly, and congenital thumb hypoplasia.
General head to toe examination
- General Appearance: Alert, co-operative, noticeably small for age, severe waxy pallor, multiple skin patches.
- Vitals:
- Heart Rate: 122 beats/minute, regular, hyperdynamic.
- Respiratory Rate: 24 breaths/minute, regular.
- Blood Pressure: $92/58\text{ mmHg}$ ($50^{\text{th}}$ centile, normotensive).
- Temperature: $37.8^\circ\text{C}$ ($100.0^\circ\text{F}$) axillary.
- Capillary Refill Time: $<2$ seconds.
- Anthropometry:
| Parameter | Observed | Expected (50th WHO) | Z-score / Centile | Inference |
|---|---|---|---|---|
| Weight | 16.5 kg | 23.0 kg | $<-3.0\text{ SD}$ | Severe Underweight |
| Height | 108.0 cm | 122.0 cm | $<-3.0\text{ SD}$ | Severe Short Stature (Stunting) |
| Head Circumference | 47.5 cm | 51.5 cm | $<-3.0\text{ SD}$ | Microcephaly |
| BMI | $14.1\text{ kg/m}^2$ | $15.5\text{ kg/m}^2$ | $-1.2\text{ SD}$ | Mild thinness |
- Dysmorphic Physical Features (Fanconi Phenotype):
- Radial Ray & Skeletal Defects:
- Right Hand: Marked hypoplasia of the right thumb (Type II Thumb Hypoplasia): thumb is short, slender, with advective weakness and absent thenar eminence; radius intact, no radial club hand. Left thumb is normal.
- Cutaneous Findings:
- Café-au-lait Macules: Four distinct, oval, light-brown macules with smooth borders ('coast of California') measuring $>1.5\text{ cm}$ over the trunk and right thigh.
- Generalized bronze-brown mottled hyperpigmentation over the neck, axillae, and groin.
- Facial Dysmorphism: Triangular facies, small chin (micrognathia), epicanthal folds, and narrow palpebral fissures (microphthalmia).
- Lymphadenopathy: Completely absent. No palpable cervical, axillary, epitrochlear, or inguinal lymph nodes.
- Bony Tenderness: Sternum and anterior tibiae are completely non-tender.
- External Genitalia: Normal male phallus; bilateral small testes (1.5 mL) in scrotum (mild testicular hypoplasia).
- Radial Ray & Skeletal Defects:
Systemic Examination
Abdomen
- Inspection: Scaphoid, soft, non-tender, no distension, no visible peristalsis or dilated veins.
- Palpation:
- Liver: Not palpable below costal margin; liver span 7.5 cm (normal for age).
- Spleen: MUST BE COMPLETELY NON-PALPABLE; no splenic dullness.
- No palpable retroperitoneal lumps or masses.
- Percussion & Auscultation: Normal tympanitic note; bowel sounds normal (4/min).
Cardiovascular System
- Apical impulse in 4th intercostal space midclavicular line; hyperdynamic circulation.
- Auscultation: $S_1, S_2$ normal; Grade 2/6 soft systolic hemic flow murmur heard at pulmonary area and lower left sternal border; no clicks, gallops, or friction rubs.
Respiratory System
- Normal vesicular breath sounds bilaterally; clear chest, no crackles or wheezes.
Central Nervous System
- Alert, oriented, intact cranial nerves I to XII.
- Motor tone normal, power 5/5 throughout, deep tendon reflexes $2+$ symmetrical, plantars flexor.
- Fundus examination: Pale retinal background, no papilledema, scattered small flame-shaped retinal hemorrhages (thrombocytopenic retinopathy).
Summary
Master Ishan, a 7-year-old male child born of consanguineous parents with SGA birth weight, microcephaly, congenital right thumb hypoplasia, café-au-lait spots, and short stature, presents with a 3-month insidious history of pancytopenia (severe pallor, mucocutaneous bleeding, intermittent fever) in the absolute absence of lymphadenopathy, organomegaly, or bone pain.
Final Clinical Diagnosis: Severe Aplastic Anemia (SAA) secondary to Fanconi Anemia (Constitutional / Inherited Bone Marrow Failure Syndrome), fulfilled by Modified Camitta criteria (severe pancytopenia with hypocellular marrow), requiring confirmatory Chromosomal Breakage Analysis (DEB test).
Differential Diagnosis
| Disorder | Points IN FAVOR | Points AGAINST |
|---|---|---|
| Fanconi Anemia with SAA | Onset at 7y; pancytopenia; microcephaly, short stature, hypoplastic thumb, café-au-lait spots, consanguinity; zero organomegaly | Primary Diagnosis |
| Acquired Idiopathic Aplastic Anemia | Pancytopenia, hypocellular marrow, absent organomegaly or lymphadenopathy | Does not account for thumb hypoplasia, microcephaly, short stature, or café-au-lait spots |
| Aleukemic ALL | Pancytopenia, pallor, bleeding, fever | ALL almost always has organomegaly, generalized rubbery lymphadenopathy, and severe bone tenderness; dysmorphic signs absent |
| Dyskeratosis Congenita | Inherited bone marrow failure, hyperpigmentation | Lacks classic triad: oral leukoplakia, reticular skin pigmentation, and nail dystrophy |
| Severe Megaloblastic Anemia | Pancytopenia, severe pallor | Typically has knuckle hyperpigmentation, smooth beefy tongue, neurological signs, and hypercellular megaloblastic marrow |
Investigation Protocol & Diagnostic Workup
flowchart TD
    A["Child with Pancytopenia, Absent Organomegaly & Radial Ray/Skin Anomalies"] --> B["CBC, Reticulocyte Count & Peripheral Smear"]
    B --> C["Bone Marrow Aspiration & Trephine Biopsy: Assess Cellularity & Exclude Blasts"]
    C --> D{"Camitta Criteria Fulfilled (Cellularity < 25%, ANC < 500, Plt < 20k, ARC < 60k)?"}
    D -->|Yes| E["Diagnose Severe Aplastic Anemia (SAA)"]
    E --> F["MANDATORY: Diepoxybutane (DEB) / Mitomycin C Chromosomal Breakage Test"]
    F --> G{"Increased Chromosomal Breaks & Radials?"}
    G -->|Yes| H["Confirm Fanconi Anemia: Send FANCA/C/G Genetic Panel"]
    H --> I["HLA-Typing of Patient, Parents & Sibling (Screen for MSD)"]
    I --> J{"10/10 HLA-Matched Sibling Donor Available?"}
    J -->|Yes| K["Curative Allogeneic Hematopoietic Stem Cell Transplantation (Reduced-Intensity Conditioning)"]
    J -->|No| L["Alternative: Matched Unrelated Donor HSCT vs Androgens (Oxymetholone) + G-CSF"]
1. Hematological & Bone Marrow Evaluation
- Complete Blood Count (CBC):
- Hemoglobin: $4.8\text{ g/dL}$ (Severe macrocytic anemia, MCV $104\text{ fL}$; macrocytosis is an early hallmark of Fanconi anemia; reference $11.5-13.5\text{ g/dL}$).
- Total Leukocyte Count (TLC): $1,800/\mu\text{L}$ (Marked leukopenia; reference $5,000-12,000/\mu\text{L}$).
- Absolute Neutrophil Count (ANC): $420/\mu\text{L}$ (Criteria for SAA: $<500/\mu\text{L}$).
- Platelet Count: $14,000/\mu\text{L}$ (Criteria for SAA: $<20,000/\mu\text{L}$; reference $150,000-450,000/\mu\text{L}$).
- Absolute Reticulocyte Count (ARC): Reticulocyte count $0.4\%$; ARC $16,000/\mu\text{L}$ (Criteria for SAA: $<60,000/\mu\text{L}$; reference $50,000-120,000/\mu\text{L}$).
- Bone Marrow Trephine Biopsy:
- Markedly hypocellular marrow with cellularity $<15\%$ (Normal for age is $70\%$).
- Marrow space replaced predominantly by empty fat vacuoles (adipocytes) and loose connective tissue.
- Residual lymphocytes and plasma cells visible; no leukemic blasts, no granulomas, no storage cells, no reticulin fibrosis.
- Fulfills Modified Camitta Criteria for Severe Aplastic Anemia (SAA).
2. Confirmatory Genetic & Chromosomal Diagnostics
- Chromosomal Breakage Analysis (DEB Test):
- Peripheral blood T-lymphocytes cultured with Diepoxybutane (DEB) and Mitomycin C (MMC).
- Results show a 12-fold increase in chromosomal breaks, gaps, and multiradial chromosomes (triradials and quadriradials) compared to normal control.
- Diagnostic Conclusion: Confirms Fanconi Anemia.
- Next-Generation Sequencing (Fanconi Panel):
- Identifies homozygous pathogenic mutation in the $FANCA$ gene on chromosome $16q24.3$.
3. Organ & Endocrine Screening in Fanconi Anemia
- Renal Ultrasound: Demonstrates a pelvic ectopic left kidney; right kidney normal.
- Audiometry: Mild bilateral conductive hearing loss.
- Endocrine Screen: Free T4 $0.9\text{ ng/dL}$, TSH $4.2\text{ mIU/L}$ (normal); fasting blood glucose normal.
Definitive Therapeutic Management Plan
1. Transfusion Rules in a Potential HSCT Candidate (VIVA TRAP)
- Strict Rule: Minimize all red cell and platelet transfusions to prevent alloimmunization.
- When transfusions are life-saving:
- Use strictly Leukodepleted and Irradiated blood products (prevents CMV transmission and transfusion-associated GVHD).
- NEVER use directed blood products from the parents, siblings, or blood relatives! Transfusion of family blood sensitizes the patient to minor histocompatibility antigens, dramatically elevating the risk of primary graft rejection during subsequent bone marrow transplantation!
2. Curative Hematopoietic Stem Cell Transplantation (HSCT)
- Donor Search: Stat high-resolution HLA typing performed on the patient and his 3-year-old brother.
- If 10/10 Matched Sibling Donor (MSD) is Identified:
- Allogeneic HSCT is the Definitive First-Line Curative Therapy.
- Conditioning Regimen in Fanconi Anemia (CRITICAL VIVA TRAP):
- Standard myeloablative conditioning (high-dose cyclophosphamide $200\text{ mg/kg}$ or full-dose irradiation) is LETHAL in Fanconi anemia due to extreme cellular hypersensitivity to DNA damage!
- Must utilize Reduced-Intensity Conditioning (RIC): Low-dose Cyclophosphamide ($40-60\text{ mg/kg}$) + Fludarabine ($120-150\text{ mg/m}^2$) + Anti-Thymocyte Globulin (ATG).
- If No Matched Sibling Donor (MSD) Exists:
- Standard Immunosuppressive Therapy (Horse ATG + Cyclosporine) has very poor response rates ($<25\%$) in Fanconi anemia.
- Perform an urgent 10/10 Matched Unrelated Donor (MUD) search.
- Medical Bridge: Synthetic Androgens: Oxymetholone ($1.0\text{ to } 2.0\text{ mg/kg/day}$ orally) + low-dose oral steroids to stimulate residual erythropoietin and megakaryopoiesis. Monitor closely for hepatotoxicity, peliosis hepatis, and hepatic adenomas.